


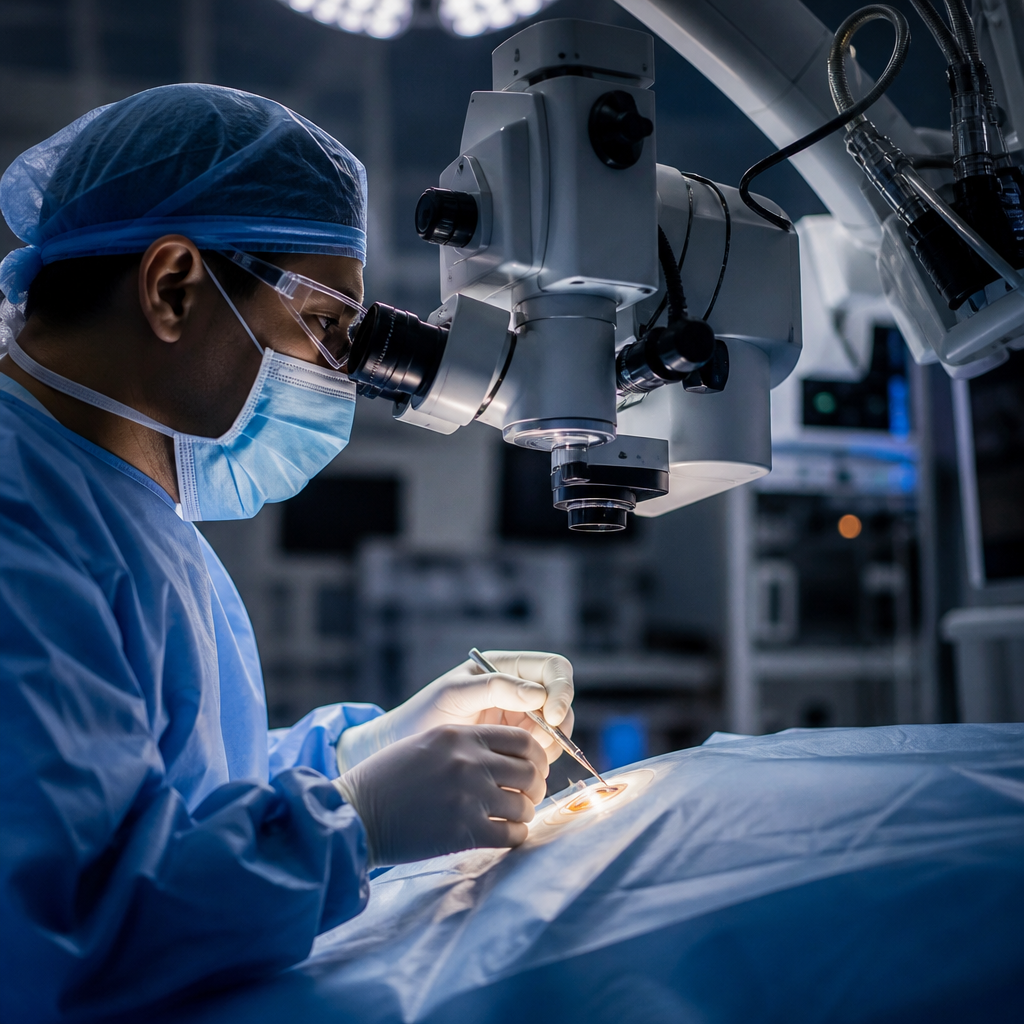
Precision, risk management, and strategic resource allocation define successful operations whether you’re managing a manufacturing floor or a surgical suite. The parallels between operational efficiency in business and the practice of ophthalmology reveal surprising insights about how specialists approach complex procedures under constraint. Both fields demand meticulous planning, real-time decision-making, and the ability to adapt protocols when circumstances shift unexpectedly.
The Economics of Precision Medicine
Eye surgery represents one of the most capital-intensive medical specializations, requiring equipment that can cost hundreds of thousands of dollars and technicians trained to operate within tolerances measured in microns. This investment structure forces ophthalmology practices to think like operations managers, balancing utilization rates against patient outcomes while maintaining strict quality standards. A single laser system for vision correction might serve thirty patients per week, but each procedure requires specific calibration, sterile protocols, and recovery monitoring that creates operational bottlenecks similar to those found in precision manufacturing.
The financial model resembles high-mix, low-volume production. Cataract procedures differ from refractive corrections, which differ from glaucoma interventions. Each requires distinct instrument sets, different recovery protocols, and varying time allocations. Practices must forecast demand across multiple procedure types while managing inventory for consumables like intraocular lenses, surgical drapes, and pharmaceutical supplies that have strict expiration dates and storage requirements.
Risk Stratification and Decision Trees
Before any surgical procedure, ophthalmologists conduct extensive risk assessments that mirror the decision frameworks used in operational planning. Patient age, corneal thickness, existing conditions like diabetes or hypertension, and previous eye trauma all factor into whether a procedure should proceed and which technique offers the best risk-reward profile. This resembles the way operations managers evaluate make-versus-buy decisions or assess whether to automate a production line based on volume forecasts and capital availability.
Consider the decision tree for premium lens implantation during cataract surgery. Standard monofocal lenses correct distance vision but require reading glasses afterward. Multifocal or accommodating lenses reduce dependence on corrective eyewear but introduce trade-offs in night vision and contrast sensitivity. Extended depth-of-focus lenses split the difference but work best for patients with specific lifestyle requirements. The ophthalmologist must weigh patient expectations, anatomical factors, and cost considerations to recommend the optimal solution—much like an engineer selecting components for a system with competing performance requirements.
Protocol Standardization Versus Customization
Surgical centers operate under standardized protocols for efficiency and safety, yet every patient presents unique variables. This tension between standardization and customization appears throughout operational contexts. Toyota’s production system emphasizes standard work but builds in mechanisms for workers to stop the line when they spot defects. Similarly, ophthalmologists follow established surgical sequences while remaining prepared to modify their approach when tissue response deviates from expected parameters.
The concept of liquidity density in financial markets offers an analogy: concentrations of available resources enable rapid execution when opportunities arise. In surgical settings, instrument placement, staff positioning, and backup equipment availability create operational liquidity that allows the surgeon to respond immediately to complications without workflow disruption.
When Posterior Segment Procedures Demand Specialized Expertise
The back of the eye—the retina, vitreous, and associated structures—presents some of the most technically demanding surgical challenges in ophthalmology. Conditions like retinal detachment, macular holes, and diabetic retinopathy require interventions that operate at the limits of what microsurgical instruments can achieve. These procedures involve removing the vitreous gel, repairing delicate retinal tissue, and sometimes injecting gas or oil to hold repairs in place during healing. Patients experiencing symptoms like sudden floaters, flashing lights, or a curtain-like shadow in their vision need prompt evaluation, as delays can result in permanent vision loss. For those seeking to understand these complex interventions, educational resources about retina surgery provide detailed explanations of diagnostic criteria, surgical techniques, and what patients can expect during recovery periods that may extend several weeks.
The skills required for posterior segment surgery don’t transfer easily from other ophthalmic procedures. A surgeon proficient in cataract extraction works in the anterior chamber with relatively sturdy structures. Retinal surgery demands three-dimensional spatial reasoning while viewing through microscopes and indirect ophthalmoscopes, manipulating instruments that exert force measured in milligrams across tissue thinner than printer paper. This specialization mirrors how operations in different industries require distinct expertise—a process engineer optimizing chemical reactions faces fundamentally different challenges than one managing discrete part assembly, even though both apply systems thinking.
Learning Curves and Skill Acquisition
Ophthalmology training follows a steep learning curve with clearly defined progression stages. Residents begin with observation, advance to assisting, then perform procedures under supervision before gaining independence. The learning curve for vitrectomy procedures is particularly demanding, requiring hundreds of supervised cases before a surgeon achieves consistent outcomes. This structured skill development resembles apprenticeship models in manufacturing trades, where machinists spend years mastering increasingly complex operations before programming CNC systems or setting up multi-axis mills.
Simulator technology has compressed some training timelines. Virtual reality systems now allow residents to practice intraocular maneuvers without patient risk, building muscle memory and spatial awareness before entering the operating room. The simulation approach mirrors how airlines use flight simulators to train pilots in emergency scenarios too dangerous to practice in actual aircraft. Both applications recognize that expertise requires repetition under varied conditions, but safety and resource constraints make real-world practice impractical for early-stage learners.
Technology Adoption Cycles and Market Dynamics
Ophthalmology demonstrates rapid technology adoption compared to many medical specializations. Femtosecond lasers, originally developed for industrial applications, found their way into cataract surgery within a decade of FDA approval. Optical coherence tomography, which provides cross-sectional imaging of retinal layers, became standard diagnostic equipment within fifteen years of commercialization. This adoption rate reflects strong economic incentives—new technology can improve outcomes, reduce complications, and differentiate practices in competitive markets.
However, technology adoption creates operational challenges. Staff require training on new equipment. Workflow processes must adapt to accommodate different procedure steps. Patient education materials need updating to explain new options. The practice must decide whether to phase in technology gradually or commit to wholesale replacement of existing systems. These decisions involve capital budgeting, financing options, and forecasts of how quickly patients will adopt premium services—the same considerations facing any business evaluating whether to modernize production equipment or stick with depreciated assets that still function adequately.
Quality Metrics and Continuous Improvement
Surgical outcomes are measured through specific metrics: visual acuity results, complication rates, enhancement procedures required, and patient-reported satisfaction scores. Leading practices track these metrics by surgeon, by procedure type, and over time to identify trends and improvement opportunities. This data-driven approach to quality management parallels Six Sigma methodologies in manufacturing, where defect rates and process variation receive constant monitoring and analysis.
The challenge lies in distinguishing between controllable process factors and patient-specific variables. A surgeon might achieve excellent outcomes on straightforward cases but face higher complication rates when treating patients with complex medical histories. Risk adjustment becomes necessary to make fair comparisons, just as manufacturing quality analysts must account for raw material variability when assessing process capability.
Looking Through the Operational Lens
The intersection of medicine and operations reveals how universal principles of efficiency, quality, and resource management apply across seemingly different domains. Ophthalmology practices face the same fundamental challenges as any operation: managing capacity, controlling costs, maintaining quality standards, and adapting to technological change. The stakes differ—vision loss carries consequences beyond production defects—but the analytical frameworks for addressing these challenges overlap substantially. Understanding how surgical teams optimize performance under constraint offers lessons applicable to anyone managing complex operations where precision matters and failure carries significant cost.
